Ataşehir Mah. Feza Sk. No:3 İstanbul / Türkiye
 English
Introduction
Breastfeeding after breast surgery is a common concern for women considering augmentation. Many patients plan to have children after their procedure. Understanding how breast implants affect nursing ability helps patients plan confidently. The good news is that most women can breastfeed successfully after augmentation. Several factors influence the outcome including surgical technique and implant placement. This article examines the evidence around breastfeeding after breast surgery. It covers implant placement, incision techniques and milk supply considerations. It also explains what patients can discuss with their surgeon before the procedure. Informed planning supports both aesthetic goals and future family plans effectively.
Can You Breastfeed After Breast Augmentation?
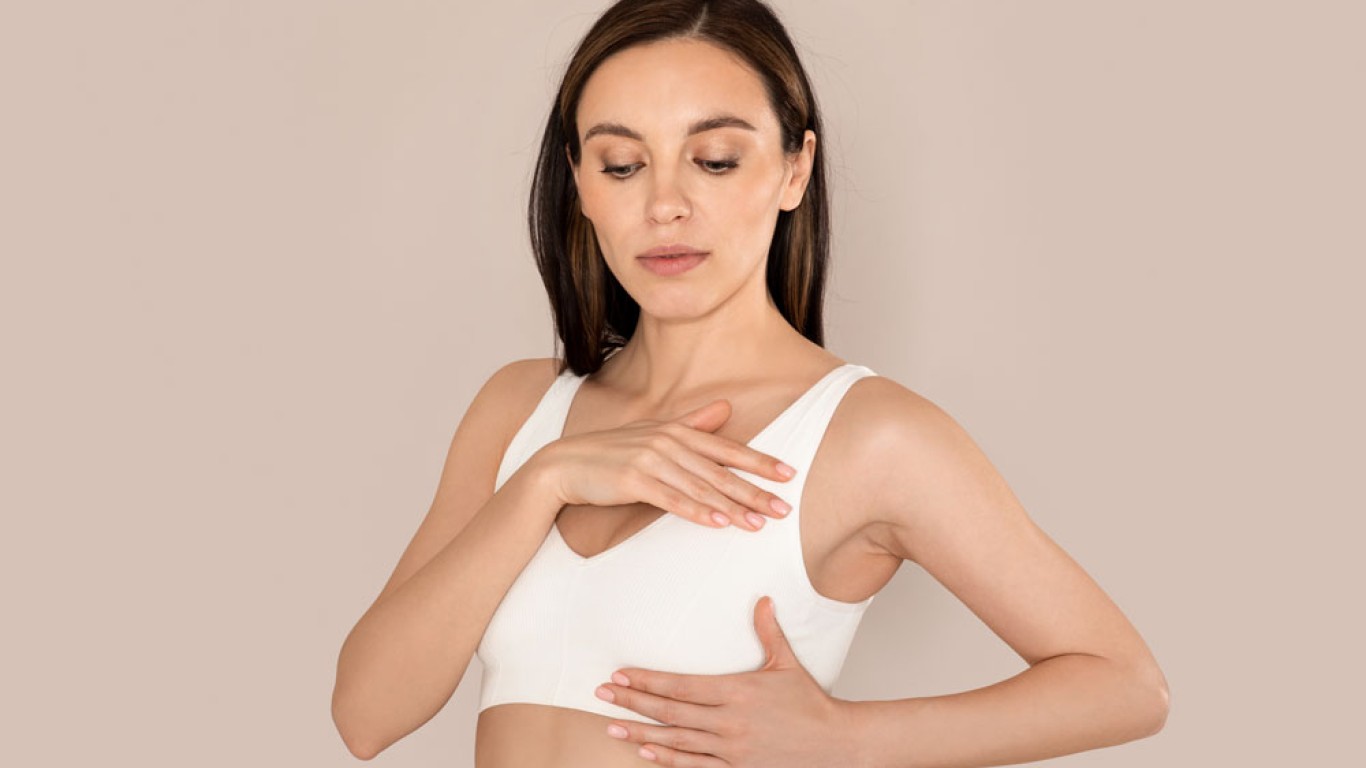
Most women can breastfeed successfully after breast augmentation surgery. Studies indicate that the majority of augmented women produce sufficient milk for nursing. Breast implants do not block or replace the mammary glands responsible for milk production. The glandular tissue that produces milk generally remains intact after surgery. Breastfeeding after breast surgery depends on several individual factors. Surgical technique plays an important role in preserving nursing function. Implant placement relative to the breast tissue also influences outcomes. Women who could breastfeed before surgery can typically do so afterwards. Those who experienced difficulties before augmentation may face similar challenges. Professional lactation support after delivery helps optimise breastfeeding success. Most surgeons discuss nursing considerations during the consultation process.
How Implant Placement Affects Breastfeeding After Breast Surgery
Implant placement is one of the most important factors for breastfeeding after breast surgery. There are two primary placement options available to patients. Submuscular placement positions the implant beneath the chest muscle. This approach keeps the implant away from the breast glandular tissue entirely. Subglandular placement positions the implant between the muscle and breast tissue. Submuscular placement is generally considered more favourable for future nursing. The breast tissue and milk ducts remain undisturbed by the implant below. Subglandular placement may place slightly more pressure on glandular tissue. However, most women with either placement breastfeed successfully after surgery. The surgeon discusses placement options and their implications during consultation. Individual anatomy influences which placement approach produces the best result.
Incision Techniques and Breastfeeding After Breast Surgery
The incision technique used during augmentation can influence breastfeeding after breast surgery. Several incision locations are available for breast augmentation procedures. The following table summarises each approach and its relevance to nursing.
| Incision Location | Description | Impact on Breastfeeding |
| Inframammary | Along the fold beneath the breast | Minimal impact on milk ducts and nerves |
| Transaxillary | Through the armpit | No direct contact with breast tissue |
| Periareolar | Around the lower edge of the areola | Higher risk of affecting ducts and sensation |
Inframammary and transaxillary incisions avoid direct contact with the breast tissue. These approaches carry the lowest risk of affecting milk ducts or nipple sensation. The periareolar incision passes through breast tissue near the nipple area. This approach may carry a slightly higher risk of disrupting milk ducts. Nipple sensation can also be affected which influences the let-down reflex. Patients planning future breastfeeding should discuss incision options with their surgeon.

Breastfeeding After Breast Surgery:Nipple Sensation
Nipple sensation plays an important role in breastfeeding after breast surgery. The let-down reflex releases milk when the baby latches and stimulates the nipple. This reflex depends partly on intact nerve pathways around the nipple area. Some patients experience temporary changes in nipple sensation after augmentation. Sensation typically returns as nerve pathways recover over several months. Permanent changes in sensation are uncommon but can occur in some cases. Reduced sensation may affect the let-down reflex during nursing attempts. Patients who retain normal nipple sensation generally breastfeed without difficulty. Discussing sensation preservation with the surgeon supports informed decision-making. Surgeons experienced in breast augmentation use techniques that minimise nerve disruption.
Breastfeeding After Breast Surgery:Milk Supply Considerations
Milk supply is a primary concern for women considering breastfeeding after breast surgery. Most augmented women produce adequate milk for their baby's nutritional needs. The mammary glands responsible for milk production remain intact after surgery. Implants do not interfere with the hormonal signals that stimulate milk production. Some women may experience a slight reduction in initial milk supply after augmentation. This is more common with periareolar incisions or subglandular placement. Supplementation with formula can support the baby if supply is initially lower. Professional lactation consultants provide practical support during early breastfeeding attempts. Milk supply often improves over the first few weeks of consistent nursing. Breast pump use alongside direct feeding can help stimulate additional milk production. Most women who commit to breastfeeding achieve successful nursing after augmentation.
Planning Breast Augmentation Before Having Children
Many women choose breast augmentation before starting a family. Discussing future breastfeeding plans with the surgeon is advisable during consultation. The surgeon can select techniques that prioritise preservation of nursing function. Submuscular implant placement is often recommended for patients planning future pregnancies. Inframammary or transaxillary incisions avoid disruption to breast tissue and ducts. These choices support breastfeeding after breast surgery without compromising aesthetic outcomes. Patients should understand that pregnancy itself changes breast shape and volume. A second procedure may be considered after completing breastfeeding if desired. Breast augmentation does not prevent pregnancy or affect fertility in any way. Planning ahead allows patients to achieve both aesthetic and family goals confidently.
Conclusion
Breastfeeding after breast surgery is possible for most women with breast implants. Implant placement and incision technique influence nursing outcomes significantly. Submuscular placement and inframammary incisions carry the lowest risk of disruption. Nipple sensation preservation supports the let-down reflex during breastfeeding. Milk supply is usually adequate although some women may need early support. Discussing future breastfeeding plans with the surgeon ensures technique selection accounts for nursing. Research supports the safety of breast augmentation for women planning future families. Professional lactation support after delivery optimises breastfeeding success for all mothers. Turkey offers experienced breast augmentation surgeons who plan techniques around future nursing needs.
To find out more and to book a consultation visit the ACIBADEM Beauty Center Aesthetics webpage.
Frequently Asked Questions
Yes, the majority of women with breast implants can breastfeed successfully.
Submuscular placement is generally considered most favourable for nursing preservation.
Yes, inframammary and transaxillary incisions carry the lowest risk of affecting milk ducts.
Most women produce adequate milk, though some may experience a slight initial reduction.
Yes, discussing future nursing plans allows the surgeon to tailor the technique accordingly.